Why Postpartum Core Work Should Start With Breathing, Not Crunches
Quick Answer: The abdominal wall, diaphragm, pelvic floor and deep back muscles work together as a pressure-managing system. After pregnancy that system has been stretched, repositioned and de-coordinated, and crunches load the outer layer of a system whose inner layer is not yet working — which drives pressure downward and outward rather than building support. Breathing work re-establishes the coordination first. It looks like doing nothing and it is the step that makes everything afterwards effective.
It genuinely is not a gentler version of core work for people who cannot manage the real thing.
It is the part that makes the real thing work.


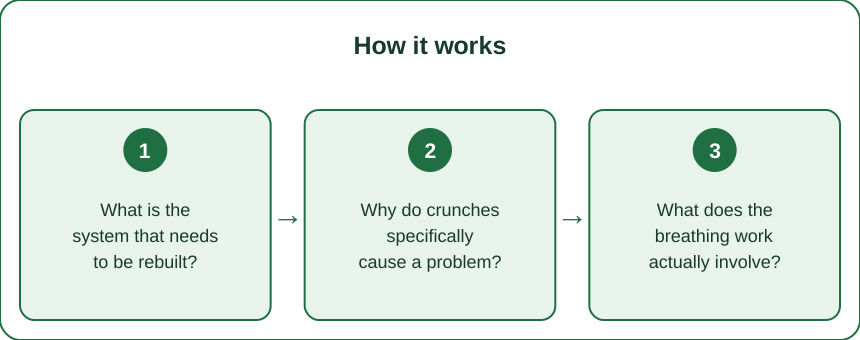
What is the system that needs to be rebuilt?
Four structures that function as a single unit, often described as a canister.
The diaphragm at the top. The pelvic floor at the bottom. The transverse abdominis wrapping around the front and sides. The deep spinal muscles at the back.
These move together with every breath. On an inhale, the diaphragm descends and the pelvic floor lengthens. On an exhale, the diaphragm rises and the pelvic floor recoils upward with the deep abdominals drawing in. This coordination happens automatically in a well-functioning system, and it is what manages pressure inside your abdomen during any effort.
What pregnancy does to it:
The abdominal wall stretches substantially, and the linea alba — the connective tissue running down the midline — widens. Some degree of separation is universal in late pregnancy.
The ribcage repositions, often flaring outward, which changes the diaphragm’s angle and how effectively it works.
The pelvic floor takes months of increasing load, and in a vaginal birth, considerable stretch.
The posture changes, and the coordination between these four structures is disrupted — they stop firing in the right relationship to each other.
So the problem after birth is rarely that the muscles are absent. It is that the timing between them has been lost, and that the system’s ability to manage pressure has been compromised.
What does that mean for exercise choice?
It means that an exercise which generates pressure — a crunch, a plank, a sit-up — is asking a system that cannot yet manage pressure to manage a lot of it. The pressure goes somewhere, and the available directions are downward onto the pelvic floor and forward through the midline.
Why do crunches specifically cause a problem?
Because of where the pressure goes when the deep system is not coordinating.
A crunch contracts the rectus abdominis — the outermost, most superficial abdominal muscle. It increases intra-abdominal pressure substantially.
If the deep system is working, that pressure is contained. If it is not:
Pressure pushes downward onto the pelvic floor, which after birth is frequently the least able to resist it. This is a plausible route to leaking, heaviness, or worsening of existing symptoms.
Pressure pushes outward through the midline, where the connective tissue is at its weakest. The visible sign is doming or coning — the abdomen forming a ridge along the centre during effort. This indicates that the load is being transferred through the connective tissue rather than being managed by muscle.
And it reinforces the wrong pattern. Repeatedly training the outer layer while the deep layer is offline teaches the body to do exactly that, which makes the underlying coordination problem more entrenched rather than less.
The doming test is the practical takeaway: during any core exercise, look at your midline. If it domes, cones or bulges, that exercise is currently too much — regardless of how it feels. It is a clear, visible signal and it applies at every stage of recovery.
This is also why the answer is not never do crunches. It is that they come later, once the system can manage the pressure, and the doming test tells you when.
Postnatal recovery varies enormously by individual and by birth. This is general information, not medical advice — a postnatal physiotherapy assessment is the appropriate starting point, and is available in many places.
What does the breathing work actually involve?
It is more specific than just breathing, and the details are what make it work.
The starting point: 360-degree breathing.
Lie on your back with knees bent, or sit supported. Place your hands on your lower ribs, thumbs toward the back.
On the inhale, aim to feel your ribs expand outward and backward into your hands, not just your belly rising. Let the pelvic floor relax and lengthen — this is the part people find counterintuitive, because so much messaging is about tightening.
On the exhale, let the ribs settle, and feel a gentle lift of the pelvic floor with a soft drawing-in low in the abdomen. Gentle — this is not a maximum contraction.
That is the whole foundation, and it is worth several weeks of practice.
Why the inhale relaxation matters: many people after birth hold the pelvic floor in a constantly gripped state, which is a form of tension rather than strength. A muscle held short cannot generate force well, and learning to fully lengthen it is often the missing piece for people whose symptoms have not improved with Kegels alone.
Then: connect breath to effort.
Exhale on the exertion. Standing up from a chair, lifting the car seat, picking up a toddler. This single habit does more for daily protection than any exercise, because it aligns the pressure management system with the moments that actually load it.
Then: add load gradually, with the breath pattern maintained and the midline watched.
How long does this stage take?
It varies enormously. Some people establish the connection in a couple of weeks; for others it takes considerably longer, particularly after a caesarean or a difficult birth. The progression is guided by the doming test and by symptoms, not by a timeline.

What does a sensible progression look like?
Broadly, and with the caveat that individual assessment beats any general sequence.
Stage one — connection. 360-degree breathing, pelvic floor relaxation and gentle engagement, exhale-on-effort in daily life. Walking as the main activity.
Stage two — connection under light load. The same breathing pattern while adding small movements: heel slides, single leg lifts with the pelvis stable, bridges. Watching the midline throughout.
Stage three — loaded movement. Squats, hip hinges, rows, presses, carries. Real strength work, with the breathing pattern maintained. This stage is where most of the recovery actually happens, and many people never reach it because they stay in gentle rehabilitation exercises indefinitely.
Stage four — impact and higher demand. Running, jumping, high-intensity work. This is the last stage, not an early one, and returning to running before the system is ready is a common source of pelvic floor problems that appear months after birth.
Throughout:
- Exhale on exertion, always.
- Watch for doming, and regress the exercise if you see it.
- Symptoms are information. Leaking, heaviness, or pain mean the current load is too much, not that you should push through.
- Progress load rather than repetitions. Strength work beats endless repetitions of gentle movements.
And the thing worth stating plainly: carrying a baby, a car seat and a changing bag is heavy lifting performed many times a day, often in poor positions and while tired. The strength you need is real strength, and the goal of this progression is to get you there, not to keep you doing gentle exercises forever.
See a postnatal physiotherapist for individual assessment, particularly for diastasis recti, prolapse symptoms, incontinence, or pain. This is general information, not medical advice.
Is there anything about this time of year worth considering?
A few practical things for the coming weeks.
Postnatal classes and groups restart in September, after the summer break. Group postnatal exercise classes with a qualified instructor are one of the better routes into stage two and three work, and they also address the isolation that makes consistency hard. This is the best few weeks of the year to find one.
Walking gets harder as weather turns, and walking is the backbone of early recovery. Having an indoor alternative planned — a home routine, a class, a treadmill — before the weather removes the outdoor option is worth doing now rather than in November.
Cough and cold season is coming, and a persistent cough is a large repeated pressure event. Learning to brace against a cough — crossing your legs, leaning slightly forward, exhaling with control — is worth practising before you need it.
Carrying gets heavier in autumn. More layers on the baby, a heavier pram, and wet slippery ground. The loads increase exactly as conditions worsen.
Vitamin D is worth asking about, particularly if breastfeeding, as production stops for the winter months in northern latitudes. That is a conversation for your GP or health visitor.
And the daylight change affects sleep, which is already the hardest variable postnatally. Morning light exposure helps, and it is worth protecting as mornings get darker.
Is it too late to start if my baby is older?
No. Postnatal recovery work is effective months and years after birth, and many people only start once they notice a symptom. The progression is the same.
This is general information, not medical advice.
FAQ: Postpartum Core Questions, Answered
When can I start?
Gentle breathing work can generally begin very early, and everything beyond that should follow your postnatal check and ideally a physiotherapy assessment. Follow the guidance you have been given.
Will my diastasis close on its own?
Some narrowing happens naturally in the months after birth. The more important measure is the tension the connective tissue can generate, not the gap width, and that responds to appropriate training.
Are planks safe?
Eventually, for many people. Not as a starting point, and the doming test is the guide.
Why does my stomach still look pregnant?
Multiple factors — connective tissue, muscle coordination, posture, and time. It is one of the most distressing aspects and it is not a reflection of effort.
Do I need to see a physio if I feel fine?
A postnatal assessment is routine in some countries and is worth seeking regardless, because problems are common and treatable and many are silent early on.
Can I lift my toddler?
Yes, and exhale as you lift, keep the load close, and use your legs. Avoiding lifting entirely is neither possible nor desirable.
TL;DR:
- The diaphragm, pelvic floor, deep abdominals and spinal muscles work as one pressure-managing system, and pregnancy de-coordinates it.
- Crunches load the outer layer while the inner layer is offline, driving pressure down onto the pelvic floor and out through the midline.
- The doming test — a ridge along the midline during effort — is the clear visible signal that an exercise is currently too much.
- Start with 360-degree breathing, including learning to fully relax the pelvic floor on the inhale.
- Exhale on exertion in daily life. It protects more than any exercise does.
- Progress to real loaded strength work — carrying a baby and a car seat is heavy lifting, and gentle exercises forever will not prepare you for it.
- Autumn restarts postnatal classes, brings cough season, and removes the walking option — plan the indoor alternative now.
This is general information, not medical advice — seek a postnatal physiotherapy assessment.
The breathing is not the warm-up for the core work. It is the part that decides whether the core work does anything.
See It in Motion
Seen here: Maternity Capris with Side Pockets — shop it on bubblelime.com
Keep Reading
This article is for general informational and styling purposes only. Fit, sizing, and product availability may vary.
