Why Postpartum Core Work Starts With Exhaling, Not Crunching
Quick Answer: Your deep core works as a pressure system - diaphragm on top, pelvic floor at the bottom, deep abdominals wrapping around - and after birth the coordination between those parts is disrupted more than the strength is. Exhaling generates the reflexive engagement of the deep abdominals and pelvic floor together, which is exactly the coordination that needs rebuilding. Crunches load the outer abdominals over a system that is not yet coordinating, which can worsen doming and pelvic floor symptoms.
Start with the breath. The visible work comes later and works better.


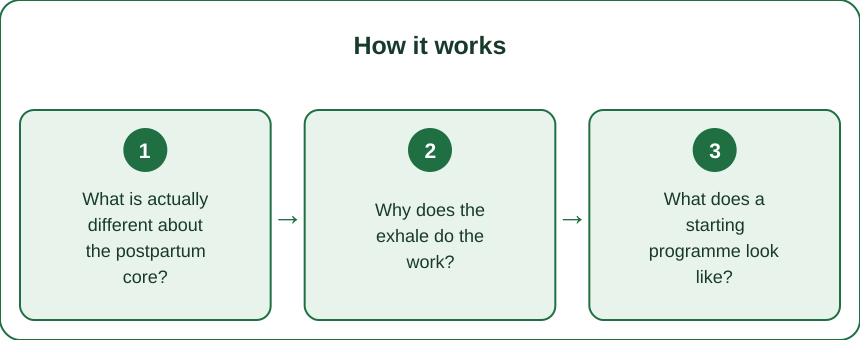
What is actually different about the postpartum core?
It is a coordination and pressure problem more than a strength problem.
The deep core is a container. The diaphragm forms the lid, the pelvic floor the base, the transverse abdominis wraps the front and sides, and the deep back muscles close it behind. These four work together to manage the pressure inside your abdomen during every movement, cough, and lift.
Pregnancy stretches the front of that container substantially. The linea alba - the connective tissue running down the midline - softens and widens to make room. Some degree of separation is universal by late pregnancy, and it narrows naturally over the months after birth for most people.
But stretched tissue does not just need shortening - it needs tension. The relevant question is not only how wide the gap is, it is whether the connective tissue can generate tension across it. A narrower gap that stays soft functions worse than a slightly wider one that holds tension.
And the timing signal gets disrupted. The deep core normally engages fractionally before movement, anticipating load. After pregnancy and birth, that anticipatory timing is commonly delayed or absent, so the outer muscles take over and the deep system stays quiet.
Which is why exercise selection matters so much here. Loading the outer abdominals over an uncoordinated deep system reinforces exactly the pattern you are trying to change.
Why does the exhale do the work?
Because it recruits the whole system reflexively, without you having to find each piece.
Exhaling naturally lifts the pelvic floor and draws in the deep abdominals. This is an automatic, reflexive coupling - you do not have to consciously contract anything for it to happen. That matters enormously when the conscious connection to those muscles is exactly what feels missing.
It reduces intra-abdominal pressure at the moment of effort. Breath-holding during exertion spikes downward pressure onto the pelvic floor and outward pressure on the healing midline. Exhaling on the effort vents that pressure, which is the single most protective habit available.
It restores the diaphragm-pelvic floor relationship. They move together - down on the inhale, up on the exhale - and pregnancy disrupts that rhythm mechanically as the growing uterus changes the diaphragm’s position. Re-establishing the rhythm is upstream of everything else.
And it trains timing rather than force. The deficit is usually in coordination and timing. Breath-led exercises train exactly that, at loads low enough that the system can actually succeed - which is how motor patterns get rebuilt.
The practical translation is simple: exhale on the hard part. Exhale as you lift the baby, as you stand up, as you push the pram uphill. This one habit does more for early recovery than any specific exercise.
What does a starting programme look like?
Small, unglamorous, and effective. Cleared with your healthcare provider first.
1. Diaphragmatic breathing, lying down. Hands on the lower ribs. Inhale and feel the ribs widen sideways - not the belly puffing up alone, and not the chest rising. Exhale slowly and completely, feeling the ribs draw down and in. Five to ten breaths, a few times a day.
2. Exhale with a gentle pelvic floor lift. On the exhale, add a light lift - the sensation of stopping wind, or drawing up gently. Light, not maximal. Release fully on the inhale. The release is as important as the lift - a pelvic floor that never fully relaxes causes its own problems.
3. Add small movement on the exhale. Heel slides, single-leg lifts to a low height, or a knee lift - performed on the exhale, with the ribs staying down. Range is dictated by what you can do without doming or losing the position.
4. Progress to loaded positions. Sitting, then standing, then during real tasks. The goal is the pattern showing up automatically when you lift the car seat, not just on a mat.
5. Then add strength work. Once the deep system coordinates reliably, standard progressive strength training is appropriate and valuable - carries, squats, rows, hip work. This is the phase people want to start at, and it works far better when it comes second.
Watch for the stop signals throughout: doming or coning along the midline, heaviness or dragging in the pelvis, leaking, pain, or any increase in bleeding. Each of those means reduce the load or the range, not push through.
This is general information, not medical advice. Get clearance from your healthcare provider before starting postpartum exercise, and see a pelvic health physiotherapist if you can - a single assessment is worth months of guessing, particularly after a caesarean or a complicated birth.

What Nobody Tells You About Postpartum Core Recovery
The gap width is not the whole story. Function - whether the tissue generates tension - matters more than millimetres. People fixate on closing a measured gap and miss that a functional, tensioned midline is the actual goal.
There is no fixed deadline. Connective tissue remodels over many months, and the six-week check is a clearance appointment, not a finish line. Progress at nine months is normal and common, and so is progress after a year with the right approach.
Breastfeeding and hormonal changes affect tissue laxity, so recovery timelines vary between people and between pregnancies for the same person. Comparing yourself to someone else’s timeline tells you almost nothing.
Traditional crunches and planks are not forbidden forever - they are inappropriate early, before the deep system coordinates. Many people return to both. The mistake is starting there, not ever doing them.
Sleep deprivation genuinely affects tissue recovery and motor learning. This is not an excuse; it is a reason to keep sessions short and frequent rather than long and occasional. Five minutes three times a day beats a 20-minute session you skip.
Constipation is a real setback. Straining loads the pelvic floor and midline hard, and it is extremely common postpartum. Addressing it is legitimate core rehab, not a separate issue.
And the one that surprises people most: progress shows up in daily life before it shows up in the mirror. Getting off the floor without using your hands, carrying the car seat without bracing, coughing without leaking. Those are the real milestones, and they arrive long before any visual change.
How do you know when to progress or step back?
Clear signals in both directions.
Signs you are ready for more: you can maintain the breath pattern through the whole exercise, no doming along the midline, no pelvic heaviness, no leaking, and the movement feels controlled rather than effortful. When an exercise feels easy for two consecutive sessions, add a small progression - more range, a longer lever, or a load.
Signs to step back: doming or coning, any leaking or heaviness, pain anywhere, an increase in bleeding, or breath-holding that you cannot avoid. Breath-holding is the most useful early warning - it means the demand exceeded what the system can manage.
Progress one variable at a time. More range, or more load, or more reps - not two together. When something goes wrong you want to know which change caused it.
Weeks, not days. Connective tissue adapts slowly. A sensible progression rate is a small increase every one to two weeks, which feels frustratingly slow and is considerably faster than repeatedly overreaching and backing off.
And revisit the basics when life changes. Illness, a bad stretch of sleep, a new pregnancy, or a period of increased lifting all warrant returning to the breath work for a week. It is a foundation you can return to, not a level you graduate from.
When to seek help rather than progress: persistent doming that does not improve, ongoing leaking beyond the early weeks, pelvic heaviness or a bulging sensation, pain during exercise or intercourse, or a separation that is not narrowing over months. A pelvic health physiotherapist can assess all of these directly, and these are exactly the situations where self-directed programmes stall for a long time.
FAQ: Postpartum Core Rehab, Answered
When can I start core work after birth?
Gentle breathing work is often appropriate early, but get clearance from your healthcare provider first - especially after a caesarean or a complicated birth. The six-week check is a clearance point, not a starting gun for everything at once.
Are crunches and planks off the table permanently?
No. They are inappropriate early, before the deep core coordinates and while the midline is still remodelling. Many people return to both later with no issue. Starting there is the mistake, not doing them eventually.
What is doming and why does it matter?
A ridge or bulge along the midline during effort. It indicates that pressure is pushing outward through the connective tissue rather than being managed by the deep system - a signal to reduce the load or range of that exercise.
How long does recovery take?
Highly variable. Connective tissue remodels over many months, and meaningful progress at nine to twelve months is entirely normal. Comparing your timeline to someone else’s is not informative.
Does the gap have to close completely?
Not necessarily. Function - whether the midline generates tension under load - matters more than the measured width. A tensioned midline with a small residual gap generally functions well.
What is the single most useful habit?
Exhaling on effort. Every lift, every stand, every time you pick up the baby. It costs nothing, it protects the pelvic floor and midline, and it rebuilds exactly the coordination that needs rebuilding.
TL;DR:
- The deep core is a pressure system - diaphragm, pelvic floor, deep abdominals - and after birth the coordination is disrupted more than the strength.
- Exhaling reflexively engages the pelvic floor and deep abdominals together, which is precisely the coordination that needs rebuilding.
- Crunches early load the outer abdominals over an uncoordinated system, which can worsen doming and pelvic symptoms.
- Start with diaphragmatic breathing, then exhale-with-lift, then small movement on the exhale, then loaded positions, then strength work.
- Exhale on the effort - lifting the baby, standing up, pushing the pram. The highest-value habit available.
- Stop signals: doming, heaviness, leaking, pain, increased bleeding, or unavoidable breath-holding.
- Function beats gap width, there is no six-week deadline, and progress shows up in daily tasks before it shows up visually.
Get clearance first, and see a pelvic health physiotherapist if you can - one assessment saves months of guessing.
This is general information, not medical advice.
See It in Motion
Seen here: Maternity Capris with Side Pockets — shop it on bubblelime.com
Keep Reading
This article is for general informational and styling purposes only. Fit, sizing, and product availability may vary.
